Inquest considerations following fatal dental infection: Evidence for the Coroner

The scope of expert evidence in dental fatalities
In the context of a Coroner’s investigation, the primary task of the dental expert witness is to provide an objective assessment of the clinical chain of events. This requires a rigorous analysis of patient records, clinical timelines, and diagnostic decisions. The expert must assist the court by identifying whether there were indicators of an evolving, life-threatening infection, such as Ludwig’s angina or mediastinitis, and whether these were identified and managed according to the clinical standards applicable at the time. This analysis often involves interpretation of complex dental clinical failure cases where systemic comorbidities or local factors may have influenced the progression of the condition.
Clinical diagnostic and documentation criteria
The expert witness must assess the clinical evidence provided in the dental records. This assessment focuses on the following key areas:
- Initial presentation and symptomatic history, including pain, swelling, and systemic signs of sepsis.
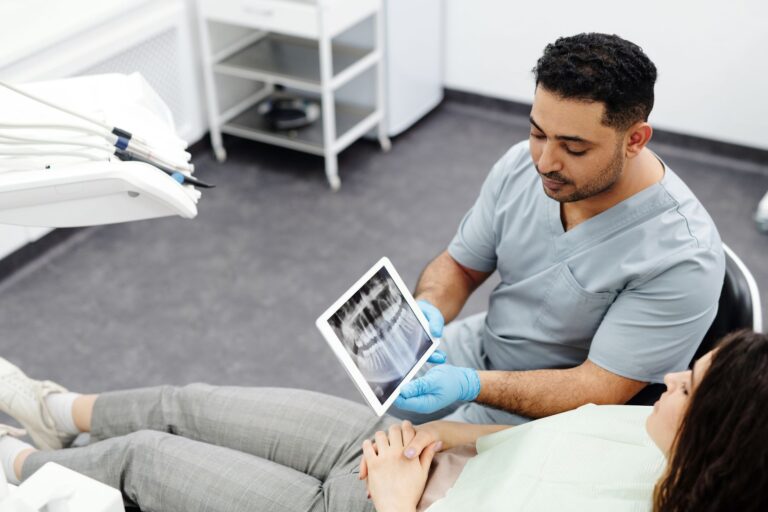
- The quality and diagnostic utility of radiographs and their role in identifying the source of infection.
- The appropriateness of the diagnostic assessment and the rationale behind any surgical or non-surgical intervention.
- The identification and documentation of warning signs, such as dysphagia, airway compromise, or pyrexia, which may indicate a need for urgent secondary care.
- The clarity and sufficiency of safety-netting advice provided to the patient post-treatment.
Under the relevant procedural rules, the expert’s overriding duty is to the court, as set out in CPR 35.3. This duty remains a cornerstone for independent expert evidence. The assessment must be grounded in the clinical standards current at the time of the treatment, rather than through the lens of hindsight, and must consider whether the management was reasonable according to a responsible body of dental practitioners, consistent with Bolam v Friern Hospital Management Committee [1957] and Bolitho v City and Hackney Health Authority [1998].
Discipline selection for inquest reporting
The selection of an appropriate expert is fundamental to the efficacy of the inquest. A fatal dental infection often involves a progression from a primary endodontic or periodontal issue to an extensive infection involving facial planes or the airway. If the fatality relates to a surgical procedure, such as a complex extraction or implant placement, an expert in oral surgery is typically required. Conversely, if the case involves endodontic failure as the primary source, a specialist in endodontics may be the most suitable. It is essential that the instructing solicitor identifies the core clinical issue early, as this dictates whether a specialist in oral and maxillofacial surgery or a dentist with substantial experience in the relevant area of practice is instructed. A fuller treatment of dental negligence is set out by Expert Search.
Evidential considerations and causation
A frequent error in preparing evidence for the Coroner is the over-reliance on the outcome as a proxy for breach of duty. The fact that a patient has died following a dental procedure does not, of itself, establish that the standard of care was sub-standard. The expert must rigorously distinguish between a known, inherent risk of a procedure and a failure in the duty of care. Furthermore, causation analysis must be carefully articulated; the expert should assist the court by evaluating whether, on the balance of probabilities, earlier intervention would have altered the outcome, consistent with the requirements for establishing factual causation.
Solicitors should ensure the following documentation is obtained and provided to the expert at the earliest opportunity:
- Complete clinical notes, including all contemporaneous entries and correspondence.
- Original digital radiographic images to allow for accurate interpretation.
- Records of any emergency department attendances or referrals.
- Documentation regarding underlying health conditions, such as diabetes or immunosuppression, which may have acted as significant risk factors.
Where the Coroner explores whether systemic failures contributed to the death, or whether there is a risk of future deaths, the expert may be asked to comment on the broader implications for the practice or clinical pathways. This is distinct from a breach of duty assessment in civil litigation. The expert should be prepared to address whether there are systemic gaps in referral pathways or emergency protocols that could be the subject of a report under regulation 28 of the Coroners (Investigations) Regulations 2013. When the court directs that a single joint expert be appointed, instructions should be provided in accordance with CPR 35.8, ensuring that the expert remains independent and focused on the evidence relevant to the inquest’s purpose.
This article is for general informational purposes only and does not constitute legal or medical advice. Readers should seek appropriate professional guidance.